




STUDY NOTES ⚕️
Clinical Presentation:
👩⚕️ Chronic cough often with hemoptysis.
👨⚕️ Pyrexia of unknown origin.
👩⚕️ Unresolved Pneumonia.
👨⚕️ Exudative pleural effusion.
👩⚕️ Asymptomatic (diagnosis on chest radiograph)
👨⚕️ Weight loss, general debility.
👩⚕️ Spontaneous Pneumonia.
Time from infection and Manifestations:
🕗 3 – 8 weeks ➡️ Primary Complex, Positive tuberculin skin test.
🕕 3 – 6 months ➡️ Meningeal, miliary and pleural disease.
🕒 Upto 3 years ➡️ Gastrointestinal, bone and joint and lymph node disease.
🕣 Around 8 years ➡️ Renal tract disease.
🕞 From 3 years onwards ➡️ Post primary disease due to reactivation or reinfection.
SOURCE: Davidson’s Principles and Practice of Medicine (19th edition)
~Sunantha✍️
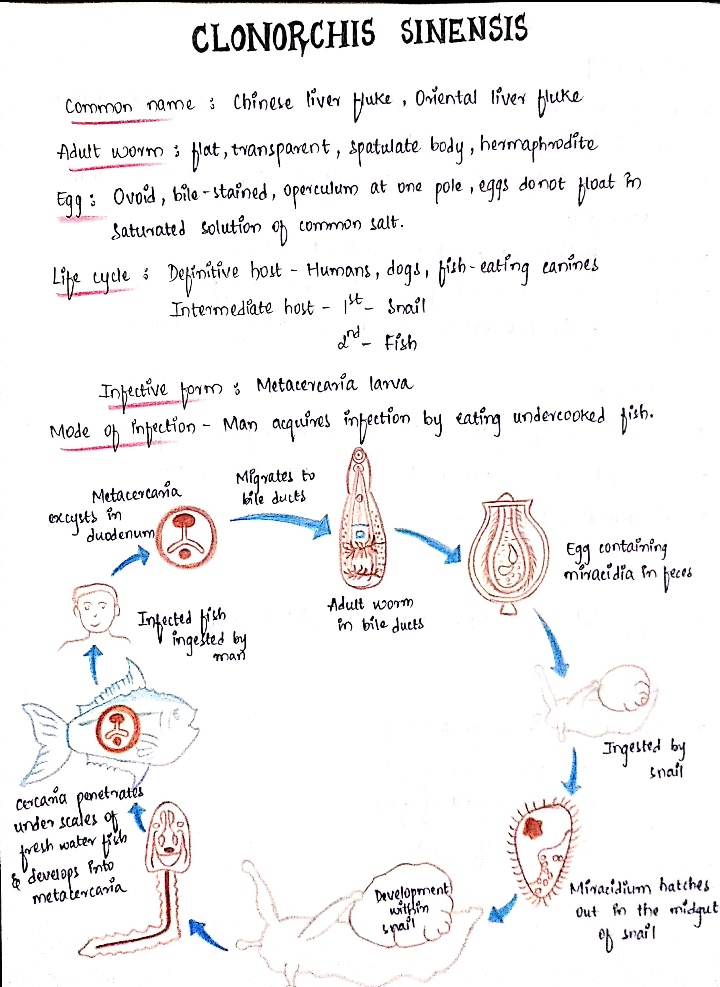
Reference : Paniker’s textbook of microbiology
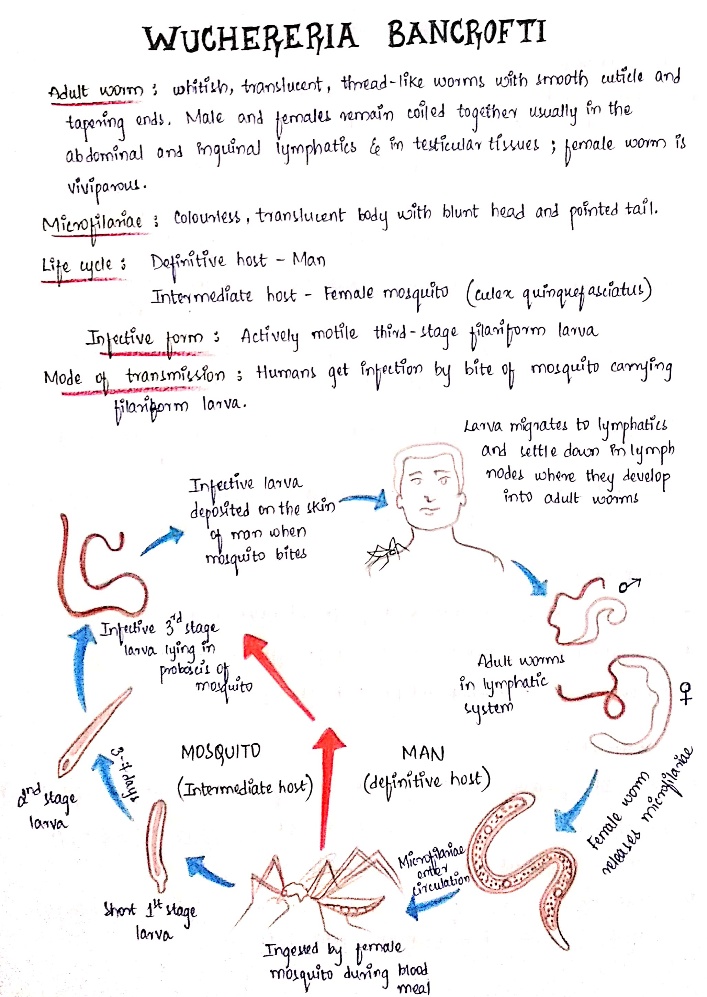


Reference : Paniker’s textbook of microbiology


The biological considerations of dental materials cannot be isolated from their physical properties.
Biological requirements of Dental Materials
A dental material should:
2. Be non-irritant to the oral or other tissues.
3. Not produce allergic reactions.
4. Not be mutagenic or carcinogenic.

Examples of hazards from chemicals in Dental Materials
✔Some dental cements are acidic and may cause pulp irritation.
✔Polymer based filling materials may contain irritating chemicals such as unreacted monomers, which can irritate the pulp.
✔Phosphoric acid is used as an etchant for enamel.
✔Mercury is used in dental amalgam, mercury vapor is toxic.
✔Dust from alginate impression materials may be inhaled, some products contain lead compounds.
✔Monomer in denture base materials is a potential irritant.
✔Some people are allergic to alloys containing nickel.
✔During grinding of beryllium containing casting alloys, inhalation of beryllium dust can cause berylliosis.
✔Some dental porcelain powders contain uranium.
✔Metallic compounds (e.g. of lead and tin) are used in elastomeric impression materials.
✔Eugenol in impression pastes can cause irritation and burning in some patients.
✔Laboratory materials have their hazards, such as: cyanide solution for electroplating, vapours from low fusing metal dies, siliceous particles in investment materials, fluxes containing fluorides, and asbestos.
✔Some periodontal dressing materials have contained asbestos fibres.
REFERENCES:
1.Textbook of Dental Materials – John J Manappallil
2.Images – Google
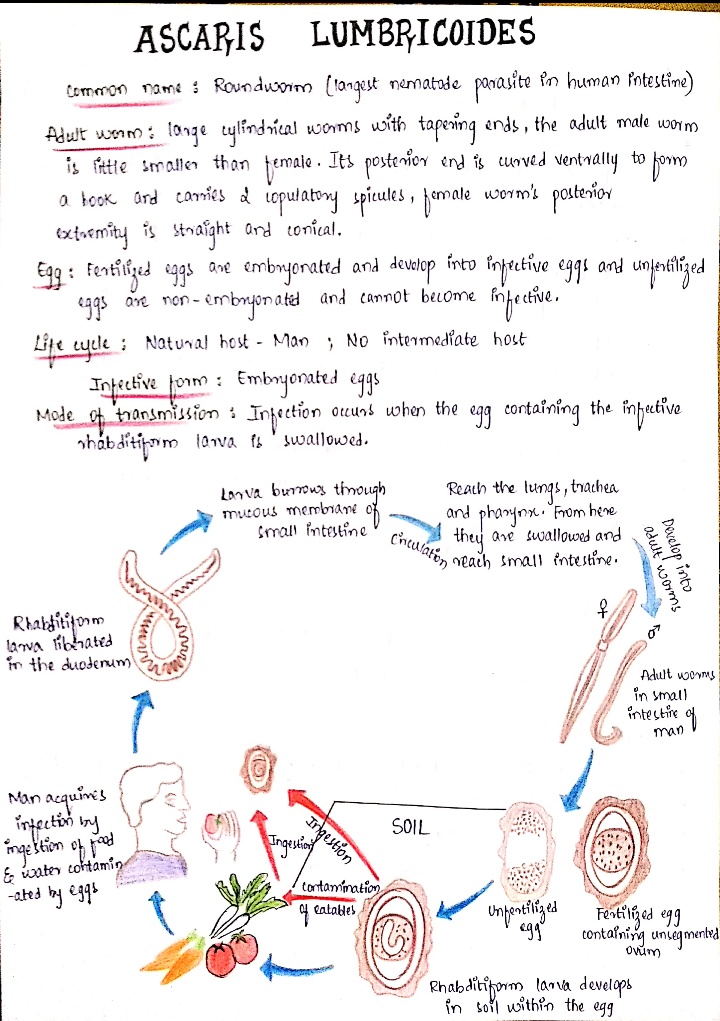
Reference : Paniker’s textbook of microbiology



🎯 GOALS…

⭐ BENEFITS ⭐
REFERENCE:- STURDEVANTS – CONS. DENTISTRY
Reference : Paniker’s textbook of microbiology


Reference : Paniker’s textbook of microbiology