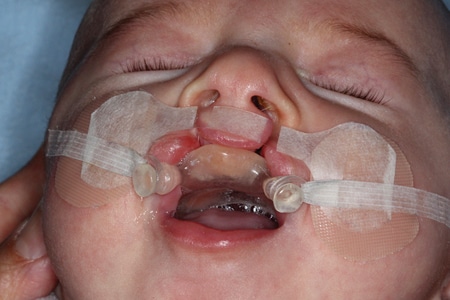
MCQs – Presurgical Nasoalveolar Molding (PNAM)

Single-Best Answer Questions

  1. The primary goal of presurgical nasoalveolar molding (PNAM) is to:
    • A. Improve facial aesthetics
    • B. Reduce the severity of the cleft
    • C. Prepare the patient for surgery
    • D. All of the above
  2. PNAM involves the use of:
    • A. A surgical plate
    • B. A molding device
    • C. A orthodontic appliance
    • D. All of the above
  3. The NAM plate is primarily used to:
    • A. Stimulate maxillary growth
    • B. Improve nasal symmetry
    • C. Correct the cleft lip
    • D. All of the above
  4. Lip massage and lip taping are recommended to:
    • A. Reduce scar tissue
    • B. Improve facial muscle function
    • C. Increase tissue elasticity
    • D. All of the above

Multiple-Choice Questions

  1. Which of the following are benefits of PNAM?
    • A. Reduced cleft stigma
    • B. Improved nasal and lip appearance
    • C. Improved maxillary growth
    • D. All of the above
  2. What are the potential challenges associated with PNAM?
    • A. Patient discomfort
    • B. Difficulty with feeding
    • C. Skin irritation
    • D. All of the above
  3. Which of the following factors may influence the effectiveness of PNAM?
    • A. Severity of the cleft
    • B. Timing of initiation
    • C. Patient compliance
    • D. All of the above

True or False Questions

  1. PNAM is a relatively new technique.
  2. The NAM plate is a permanent device.
  3. Lip massage and lip taping are only effective in the short term.
  4. PNAM can help to reduce the need for future surgeries.
  5. The long-term effects of PNAM on dental arch development are well-established.

Answers to MCQs on Presurgical Procedure for Cleft Patients

Single-Best Answer Questions

  1. B. Reduce the severity of the cleft
  2. D. All of the above
  3. A. Stimulate maxillary growth
  4. C. Increase tissue elasticity

Multiple-Choice Questions

  1. D. All of the above
  2. D. All of the above
  3. D. All of the above

True or False Questions

  1. True
  2. False
  3. False
  4. True
  5. False

MCQs on Preliminary Surgical Procedures for Cleft Patients

Single-Best Answer Questions

  1. The most common surgical procedures for cleft patients include:
    • A. Cheiloplasty, palatoplasty, and rhinoplasty
    • B. Cheiloplasty, palatoplasty, and alveolar bone grafting
    • C. Palatoplasty, rhinoplasty, and alveolar bone grafting
    • D. Cheiloplasty, rhinoplasty, and orthognathic surgery
  2. The C-flap technique is a modification of:
    • A. Millard rotation-advancement flap
    • B. Fischer’s technique
    • C. Intravelar veloplasty
    • D. Furlow palatoplasty
  3. The primary goal of postoperative care after lip surgery in cleft patients is:
    • A. To prevent infection
    • B. To promote wound healing
    • C. To improve facial aesthetics
    • D. To correct speech problems
  4. Laser therapy is used in scar management after lip surgery to:
    • A. Reduce scar tissue
    • B. Improve skin texture
    • C. Enhance wound healing
    • D. All of the above

Multiple-Choice Questions

  1. Which of the following factors influence the timing of lip and palatal repair in cleft patients?
    • A. Severity of the cleft
    • B. Patient’s age
    • C. Surgeon’s preference
    • D. All of the above
  2. What are the potential complications associated with lip surgery in cleft patients?
    • A. Dehiscence
    • B. Notching
    • C. Fistula formation
    • D. All of the above
  3. Which of the following techniques can be used for palatal repair in cleft patients?
    • A. Furlow palatoplasty
    • B. Veau-Duhamel palatoplasty
    • C. Intravelar veloplasty
    • D. All of the above

True or False Questions

  1. Lip and palatal repair are always performed simultaneously in cleft patients.
  2. The C-flap technique is a traditional method for lip repair.
  3. Postoperative massage is recommended to reduce scar tissue in cleft patients.
  4. Laser therapy is a new and experimental approach to scar management.
  5. Silicone gel can be used to help prevent scar contracture in cleft patients.

Answers to MCQs on Preliminary Surgical Procedures for Cleft Patients

Single-Best Answer Questions

  1. B. Cheiloplasty, palatoplasty, and alveolar bone grafting
  2. A. Millard rotation-advancement flap
  3. B. To promote wound healing
  4. D. All of the above

Multiple-Choice Questions

  1. D. All of the above
  2. D. All of the above
  3. D. All of the above

True or False Questions

  1. False
  2. False
  3. True
  4. False
  5. True

MCQs on Alveolar Bone Grafting for Cleft Patients #MDSOrthodontics

Single-Best Answer Questions

  1. The most common donor site for autogenous bone grafting in cleft patients is:
    • A. Tibia
    • B. Iliac crest
    • C. Radius
    • D. Femur
  2. Which of the following is the most important factor to consider when performing bone grafting in cleft patients?
    • A. Timing of the graft
    • B. Type of anesthetic used
    • C. Donor site morbidity
    • D. Post-operative care
  3. The primary purpose of bone grafting in cleft patients is to:
    • A. Improve facial aesthetics
    • B. Restore alveolar bone for future tooth movement and prosthetic restoration
    • C. Correct nasal deformities
    • D. Prevent speech problems
  4. The use of 3D planning in bone grafting for cleft patients is beneficial because:
    • A. It reduces the need for multiple surgeries
    • B. It allows for more precise graft placement
    • C. It eliminates the risk of graft failure
    • D. It ensures complete bone healing
  5. Bio-glass scaffolds are used in bone grafting for cleft patients to:
    • A. Replace the need for autogenous bone
    • B. Enhance bone regeneration
    • C. Reduce post-operative pain
    • D. Improve graft stability

Multiple-Choice Questions

  1. Which of the following factors can influence the success of bone grafting in cleft patients?
    • A. Graft volume
    • B. Graft quality
    • C. Recipient site vascularity
    • D. All of the above
  2. What are the potential complications associated with bone grafting in cleft patients?
    • A. Infection
    • B. Graft resorption
    • C. Donor site morbidity
    • D. All of the above
  3. Which of the following techniques can be used to minimize graft resorption after bone grafting in cleft patients?
    • A. Gentle handling of the bone
    • B. Use of bone marrow-derived mesenchymal stem cells
    • C. Application of growth factors
    • D. All of the above

True or False Questions

  1. The timing of bone grafting in cleft patients is a matter of consensus among clinicians.
  2. Calvarial bone is a less preferred donor site compared to the iliac crest.
  3. Crushing the bone during grafting can lead to increased resorption.
  4. 3D planning is not essential for successful bone grafting in cleft patients.
  5. Bio-glass scaffolds are a completely synthetic material that does not require autogenous bone.

Answers to MCQs on Alveolar Bone Grafting for Cleft Patients

Single-Best Answer Questions

  1. B. Iliac crest
  2. A. Timing of the graft
  3. B. Restore alveolar bone for future tooth movement and prosthetic restoration
  4. B. It allows for more precise graft placement
  5. B. Enhance bone regeneration

Multiple-Choice Questions

  1. D. All of the above
  2. D. All of the above
  3. D. All of the above

True or False Questions

  1. False
  2. False
  3. True
  4. False
  5. False

JC Presentation 2 – Prevalence of white spot lesions during orthodontic treatment with fixed appliances

Woah there, JC wizards! ‍♀️🪄 Second presentation alert, and guess who’s got your back with the ultimate slide deck? So buckle up, download that bad boy, and prepare to slay your next JC presentation like the rockstar you are!

Hey there, orthodontic peeps! Ever wondered why those pesky white spots like to crash the party on your pearly whites after getting braces? We got curious too, so we donned our detective hats ️‍♀️ and followed a group of brave souls on their brace-tastic journeys for 6 and 12 months.

The Results: Buckle up, because things are about to get interesting! At 6 months, almost half the crew (38%) had at least one white spot, and by 12 months, it climbed to a cool 46%. But hey, the good news is, the control group who hadn’t even gotten their braces on yet were practically spotless (only 11% with spots!).

The Plot Twist: Turns out, these white spots seem to prefer hanging out with the dudes! ‍ 76% of spotted teeth belonged to our male friends, while only 24% were on the ladies’ side. Who knew braces were so gender-biased?

The Takeaway: So, what’s the lesson in this orthodontic detective story? The first 6 months are like white spot central, but things kinda chill out after that. But don’t let your guard down! Clinicians gotta keep a close eye on those pearly whites, especially at the beginning, and make sure everyone’s brushing and flossing like champions to keep those spots at bay. 🪥

SOURCE FOR VIVA QUESTIONS: https://www.slideshare.net/marwanmouakeh/white-spot-lesions

Accelerating Orthodontic Treatment with Low-Level Laser Therapy

Low-level laser therapy (LLLT) has gained attention in orthodontics for its potential to accelerate orthodontic tooth movement and space closure using functional mechanics. Studies have shown that LLLT has stimulatory effects that can accelerate bone regeneration, stimulate collagen synthesis, and induce remodeling processes in oral tissues (Limpanichkul et al., 2006; Isola et al., 2019). Additionally, LLLT has demonstrated faster healing, biostimulation, and anti-inflammatory effects, which can contribute to accelerated tooth movement (Kharat et al., 2023; Basso et al., 2017). Furthermore, the effectiveness of LLLT in accelerating orthodontic tooth movement has been supported by multiple clinical trials and meta-analyses, which reported faster space closure and reduced treatment times (Miles, 2017; Sawas et al., 2023; Kalia et al., 2023).

The biostimulatory effects of LLLT have been attributed to its ability to enhance tissue repair processes, reduce inflammatory processes, and promote cell and tissue biostimulation, ultimately contributing to accelerated wound healing (Santos et al., 2021; Santana et al., 2015). Moreover, LLLT has been associated with reduced pain and improved pain control, further enhancing its potential in orthodontic treatments (Bayani et al., 2016; Topolski et al., 2018). These findings are supported by a study that concluded that LLLT was more effective in pain control compared to other methods (Topolski et al., 2018).

Furthermore, the effects of LLLT on orthodontic tooth movement have been investigated at the cellular level, revealing its biostimulatory effects and potential to enhance bone remodeling processes (Dhiman, 2018). Additionally, a study reported that LLLT was able to reduce the area of fistulous tracts, decrease inflammatory processes, and improve local vascular congestion, further highlighting its therapeutic potential in tissue healing and repair (Santos et al., 2021).

Overall, the evidence suggests that LLLT holds promise in accelerating orthodontic tooth movement and space closure using functional mechanics. Its biostimulatory effects, ability to enhance tissue repair processes, and potential to reduce pain make it a valuable adjunct in orthodontic treatments.

REFRENCES

Basso, F., Pansani, T., Cardoso, L., Citta, M., Soares, D., Scheffel, D., … & Costa, C. (2017). Epithelial cell-enhanced metabolism by low-level laser therapy and epidermal growth factor. Lasers in Medical Science, 33(2), 445-449. https://doi.org/10.1007/s10103-017-2176-z Bayani, S., Rostami, S., Ahrari, F., & Saeedi-Pouya, I. (2016). A randomized clinical trial comparing the efficacy of bite wafer and low level laser therapy in reducing pain following initial arch wire placement. Laser Therapy, 25(2), 121-129. https://doi.org/10.5978/islsm.16-or-10 Dhiman, S. (2018). Effect of low- level laser therapy (lllt) on orthodontic tooth movement – cellular level. Advances in Dentistry & Oral Health, 7(5). https://doi.org/10.19080/adoh.2018.07.555723 Isola, G., Matarese, M., Briguglio, F., Grassia, V., Picciolo, G., Fiorillo, L., … & Matarese, G. (2019). Effectiveness of low-level laser therapy during tooth movement: a randomized clinical trial. Materials, 12(13), 2187. https://doi.org/10.3390/ma12132187 Kalia, A., Bobade, S., Nene, S., Mirdehghan, N., Patil, V., & Khan, A. (2023). Evaluation of effectiveness of low level laser therapy in accelerating orthodontic tooth movement-an in vivo study. Ip Indian Journal of Orthodontics and Dentofacial Research, 9(1), 53-62. https://doi.org/10.18231/j.ijodr.2023.011 Kharat, D., Pulluri, S., Parmar, R., Choukhe, D., Shaikh, S., & Jakkan, M. (2023). Accelerated canine retraction by using mini implant with low-intensity laser therapy. Cureus. https://doi.org/10.7759/cureus.33960 Limpanichkul, W., Godfrey, K., Srisuk, N., & Rattanayatikul, C. (2006). Effects of low‐level laser therapy on the rate of orthodontic tooth movement. Orthodontics and Craniofacial Research, 9(1), 38-43. https://doi.org/10.1111/j.1601-6343.2006.00338.x Miles, P. (2017). Accelerated orthodontic treatment ‐ what’s the evidence?. Australian Dental Journal, 62(S1), 63-70. https://doi.org/10.1111/adj.12477 Santana, C., Silva, D., Deana, A., Prates, R., Souza, A., Gomes, M., … & França, C. (2015). Tissue responses to postoperative laser therapy in diabetic rats submitted to excisional wounds. Plos One, 10(4), e0122042. https://doi.org/10.1371/journal.pone.0122042 Santos, C., Guimarães, F., Barros, F., Leme, G., Silva, L., & Santos, S. (2021). Efficacy of low-level laser therapy on fistula-in-ano treatment. Abcd Arquivos Brasileiros De Cirurgia Digestiva (São Paulo), 34(1). https://doi.org/10.1590/0102-672020210001e1572 Sawas, M., Alsaghir, Z., Aldosari, F., Hafiz, R., Alghamdi, M., Alshammari, N., … & Safhi, T. (2023). Methods and technology used to accelerate dental movements in orthodontic treatments. Journal of Healthcare Sciences, 03(01), 78-83. https://doi.org/10.52533/johs.2023.30113 Topolski, F., Moro, A., Correr, G., & Schimim, S. (2018). Optimal management of orthodontic pain. Journal of Pain Research, Volume 11, 589-598. https://doi.org/10.2147/jpr.s127945

Diagnosis Demystified – Case 31

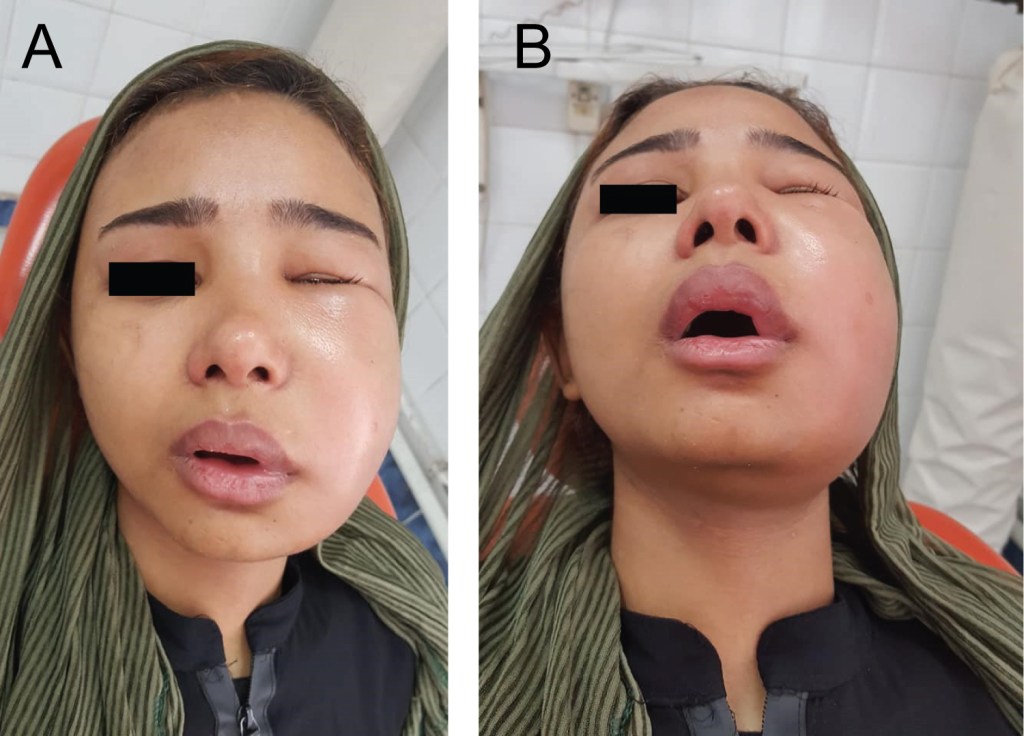
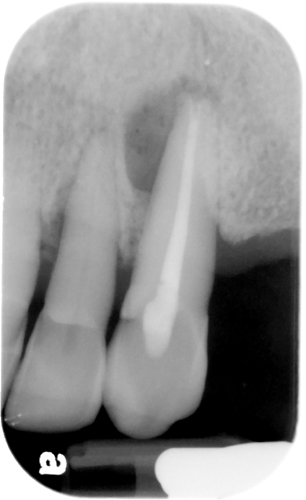
Clinically: painful, diffuse, reddened swelling affecting the right side of the face, centred on the cheek, causing partial closure of the eye. This developed overnight. The previous 3 days there had been, according to the patient, ‘an abscess’ present on UR3. The patient feels unwell and there is lymphadenopathy present. UR3 is grossly carious. Radiologically: UR3 has a periapical rarefying osteitis.

Yo, peeps! So, check this out – there’s this crazy situation going on with someone’s face, right? Like, it’s all swollen, painful, and looking like a tomato, especially on the right side, focused on the cheek. And get this, it happened overnight! 😱

So, my friend here had this “abscess” thing going on with their tooth (UR3, to be specific) for the past three days. Fast forward to now, and it’s a whole mess – they’re feeling like garbage, there’s some swollen lymph node action, and the eye on the right is only doing half its job because of the swelling.

Oh, and if you peek inside their mouth, UR3 is a total disaster zone – super decayed. And to make things even more interesting, when you take a look at it on an X-ray, there’s this periapical rarefying osteitis party happening.

Now, why am I telling you all this drama? Well, here’s the kicker – that sudden face expansion? It’s not some random curse; it’s all thanks to a not-so-friendly cellulitis causing some serious swelling. And get this, the culprit? A seemingly innocent tooth problem. Who would’ve thought, right? Moral of the story: don’t underestimate the power of a tiny toothache, it can wreak havoc on your whole face. Mind blown! 💥

In office bleaching gels containing co-doped titanium dioxide nano particles

In recent years, there has been a growing interest in the development of in-office bleaching gels containing co-doped titanium dioxide nanoparticles. Titanium dioxide (TiO2) nanoparticles have been widely studied and utilized in various applications due to their unique properties, such as high refractive index and photocatalytic activity (Kury et al., 2022). The incorporation of TiO2 nanoparticles into bleaching gels has been shown to enhance the effectiveness and safety of the bleaching process.

One study investigated the use of in-office bleaching gels containing high concentrations of hydrogen peroxide (HP) and co-doped titanium dioxide nanoparticles (Kury et al., 2022). The results showed that the incorporation of titanium dioxide nanoparticles into the bleaching gels improved their effectiveness in tooth bleaching. The photocatalytic activity of the nanoparticles enhanced the bleaching process by accelerating the chemical reaction of the hydrogen peroxide. This study highlights the potential of co-doped titanium dioxide nanoparticles in improving the performance of in-office bleaching gels.

Another study evaluated the effect of light irradiation on the bleaching process using a low-concentration hydrogen peroxide solution containing titanium dioxide as a photocatalyst (Suemori et al., 2008). The results showed that light irradiation significantly enhanced the bleaching effect of the hydrogen peroxide solution. The photocatalytic activity of titanium dioxide nanoparticles under light irradiation played a crucial role in accelerating the bleaching process. This study further supports the use of titanium dioxide nanoparticles as a photocatalyst in in-office bleaching gels.

Furthermore, the safety of in-office bleaching gels containing titanium dioxide nanoparticles has been investigated. One study evaluated a low-concentration hydrogen peroxide experimental bleaching gel containing titanium dioxide and chitosan (Ozcetin & Surmelioglu, 2020). The results showed that the gel was safe and effective for tooth bleaching. The presence of titanium dioxide nanoparticles in the gel contributed to its safety and effectiveness. This study provides evidence for the safety of in-office bleaching gels containing titanium dioxide nanoparticles.

In addition to titanium dioxide, other dopants have been explored to enhance the properties of titanium dioxide nanoparticles. For example, iron-doped titanium dioxide nanoparticles have been synthesized and studied for various applications (Abza et al., 2022). The doping of titanium dioxide with iron can modify its properties and enhance its photocatalytic activity. This suggests that co-doping titanium dioxide nanoparticles with other elements may further improve the performance of in-office bleaching gels.

Overall, the incorporation of co-doped titanium dioxide nanoparticles into in-office bleaching gels shows promise in improving the effectiveness and safety of the bleaching process. The photocatalytic activity of titanium dioxide nanoparticles enhances the bleaching process by accelerating the chemical reaction of hydrogen peroxide. Furthermore, the safety of in-office bleaching gels containing titanium dioxide nanoparticles has been demonstrated. Further research on the co-doping of titanium dioxide nanoparticles with other elements may lead to even more effective bleaching gels.

Abza, T., Saka, A., Jule, L., Gudata, L., Nagaprasad, N., & Ramaswamy, K. (2022). Synthesis and characterization of iron doped titanium dioxide (fe: tio2) nanoprecipitate at different ph values for applications of self-cleaning materials. Advances in Materials Science and Engineering, 2022, 1-9. https://doi.org/10.1155/2022/2748908 Kury, M., Hiers, R., Zhao, Y., Picolo, M., Hsieh, J., Khajotia, S., … & Cavalli, V. (2022). Novel experimental in-office bleaching gels containing co-doped titanium dioxide nanoparticles. Nanomaterials, 12(17), 2995. https://doi.org/10.3390/nano12172995 Ozcetin, H. and Surmelioglu, D. (2020). three‐month evaluation of a low concentration (6% hydrogen peroxide) experimental bleaching gel containing tio 2 and chitosan: an in vitro study. Color Research & Application, 45(6), 1101-1108. https://doi.org/10.1002/col.22543 Suemori, T., Kato, J., Nakazawa, T., Akashi, G., Igarashi, A., Hirai, Y., … & Kurata, H. (2008). Effects of light irradiation on bleaching by a 3.5% hydrogen peroxide solution containing titanium dioxide. Laser Physics Letters, 5(5), 379-383. https://doi.org/10.1002/lapl.200710137