
Author: Anisha Valli
Ortho Case 2.14
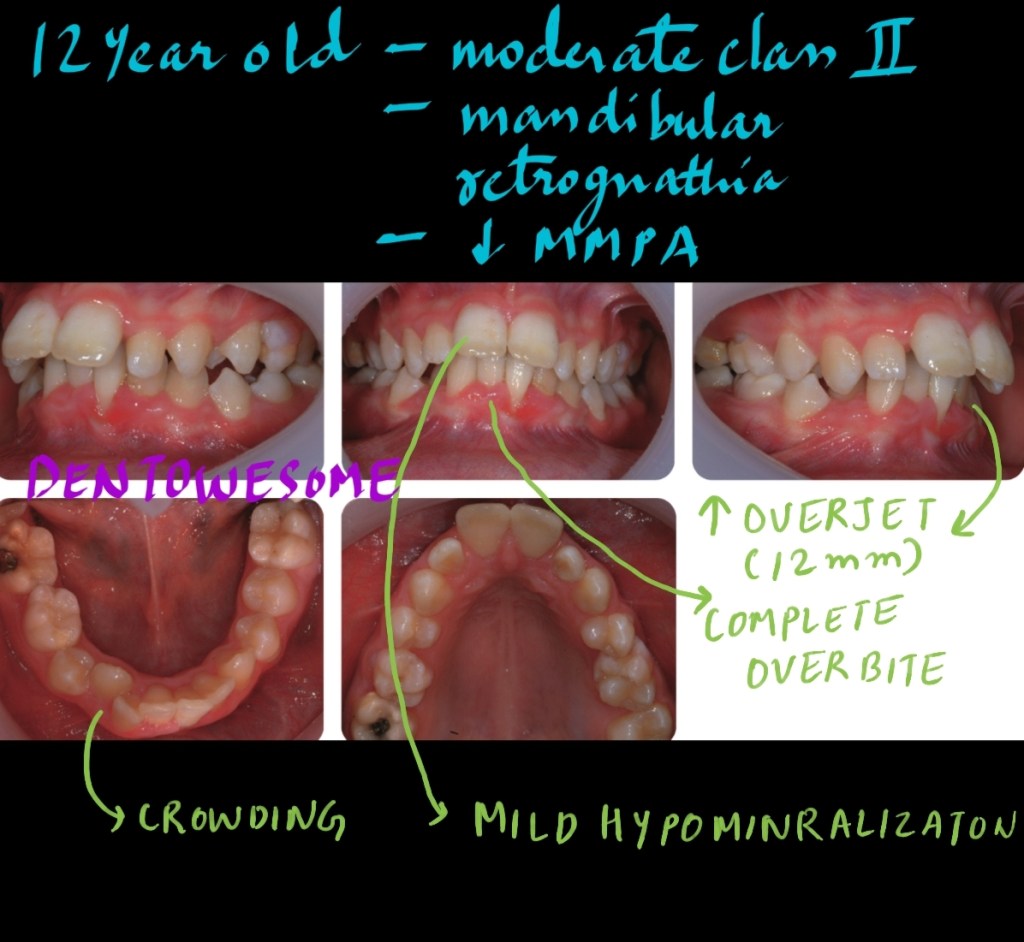
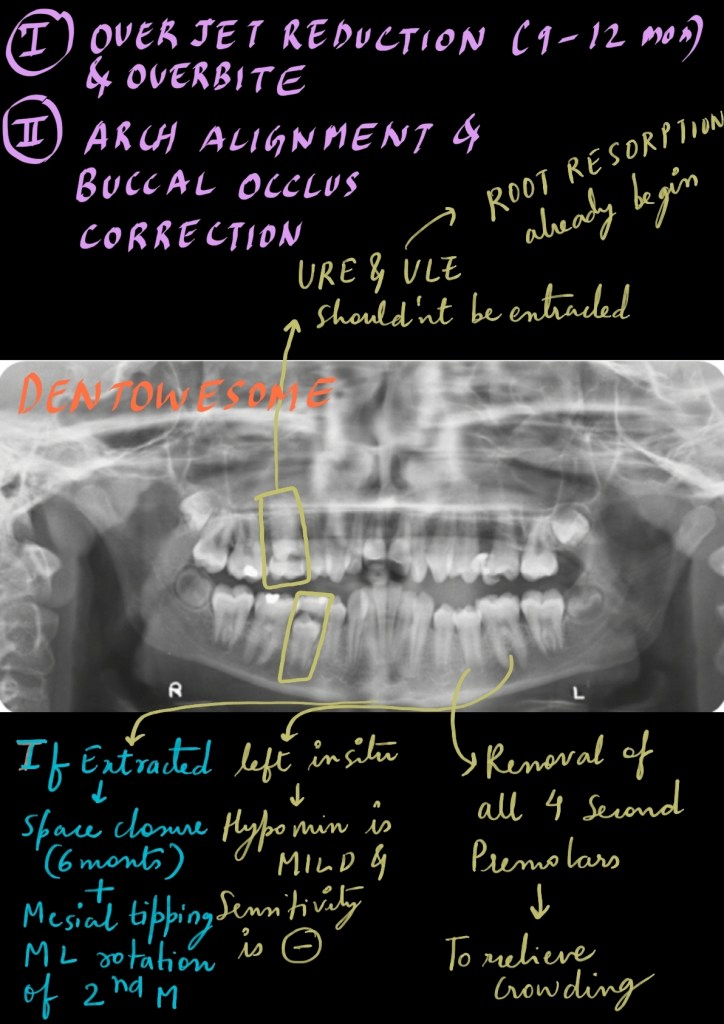
A 12-year-old female in the late mixed dentition with a class II division 1 incisor relationship on a moderate skeletal class II pattern with reduced MMPA. The malocclusion is complicated by:
• Increased overjet (12mm)
• Increased and complete overbite
• Crowding of both arches
• Mild molar–incisor hypomineralization.
Is removal of the URE, ULE and LRE indicated at this point? How would you treat this malocclusion? What are the potential orthodontic problems associated with removal of the first permanent molars? What prescription should be used during the fixed appliance phase?
I have tried my best to explain the case in the following images! Happy reading
LINK TO PDF: https://drive.google.com/file/d/1TY0almamDToyQtMMbyZ4jZxfYRMZADOk/view?usp=sharing

Ortho Case 2.13
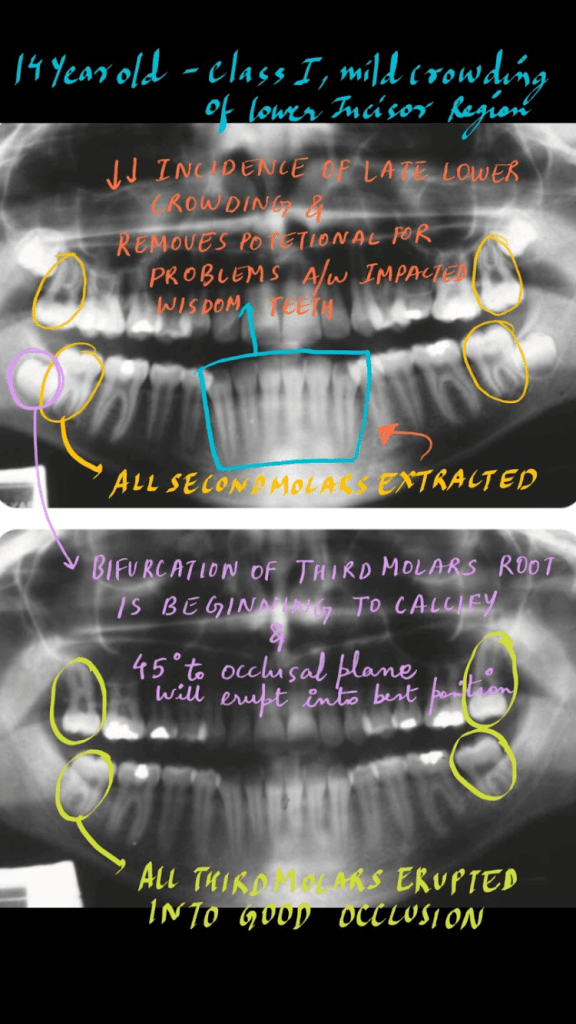
A 14-year-old male with a class I occlusion complicated by mild crowding of the lower incisor teeth
We know that we need to extract second permanent molars. What are it’s disadvantages if we go ahead with this option? Is there an optimum time to extract lower second permanent molars to obtain the best eruptive position for the third molar?
In the same way, if there was crowding in the anterior region of the maxilla. Then, What are the indications for extracting a maxillary second permanent molar?
Link: https://drive.google.com/file/d/1G4n6TZ_EOFozexnRWh08cBvncUZQ1OjS/view?usp=drivesdk
Ortho case 2.12
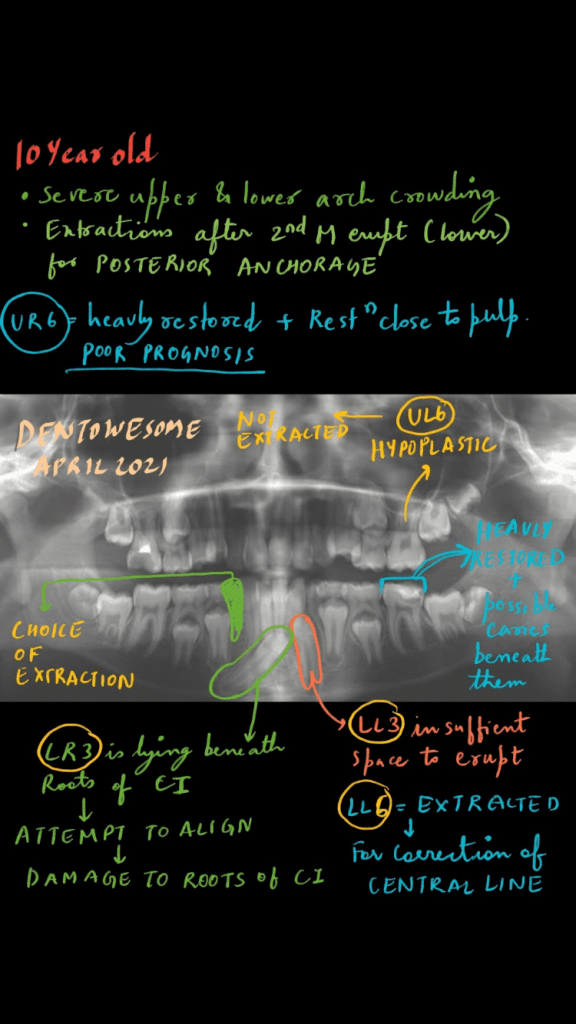
• Severe upper and lower arch crowding
• Buccally excluded UR3, impacted lower canines
• Ectopic and impacted LR3
• LR3 is excluded from the arch and ectopic in position, with its crown lying beneath the roots of the lower central incisors
• Potentially impacted LL3 due to insufficient space
• Heavily restored LL6 and UR6
• Hypoplastic UL6
• Upper and lower centre line shift to the right
How will you treat?
Link: https://drive.google.com/file/d/1UhHHaGLYLzzIeDnF_9qNTw6LrwXxbpWS/view?usp=drivesdk
Ortho Case 2.11
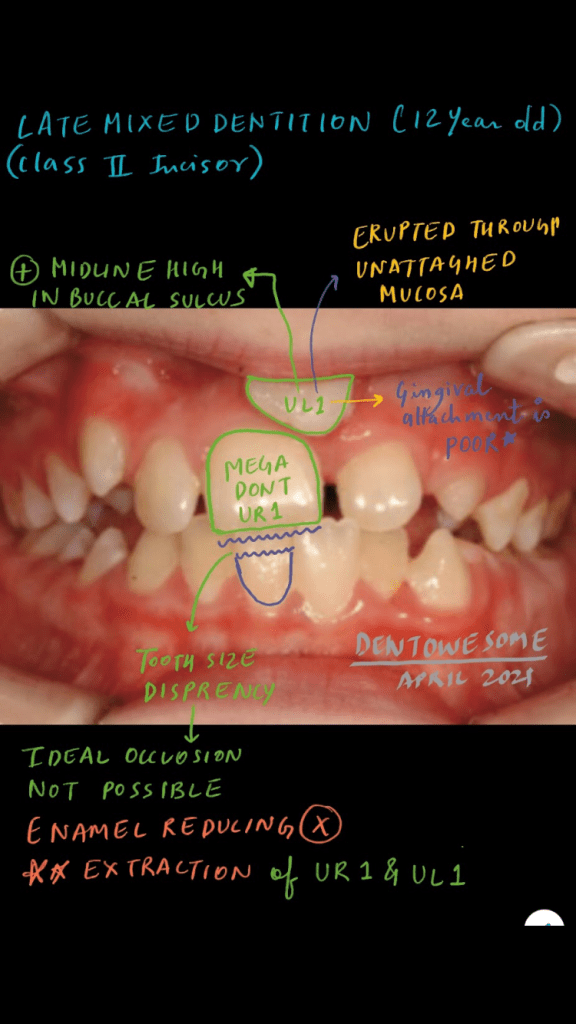
This patient presents in the late mixed dentition with a class III incisor relationship. The malocclusion is complicated by a megadont UR1 and ectopic UL1, with severe crowding in the upper arch and mild crowding in the lower arch.
Link: https://drive.google.com/file/d/1m38nWJL1X1WGyZ8peeGw9hYbIW-9crmx/view?usp=drivesdk
Ortho case 29
Link: https://drive.google.com/file/d/1UJ0ejZMn-KvpFL_Y5jmrx_hSel-acwlB/view?usp=drivesdk
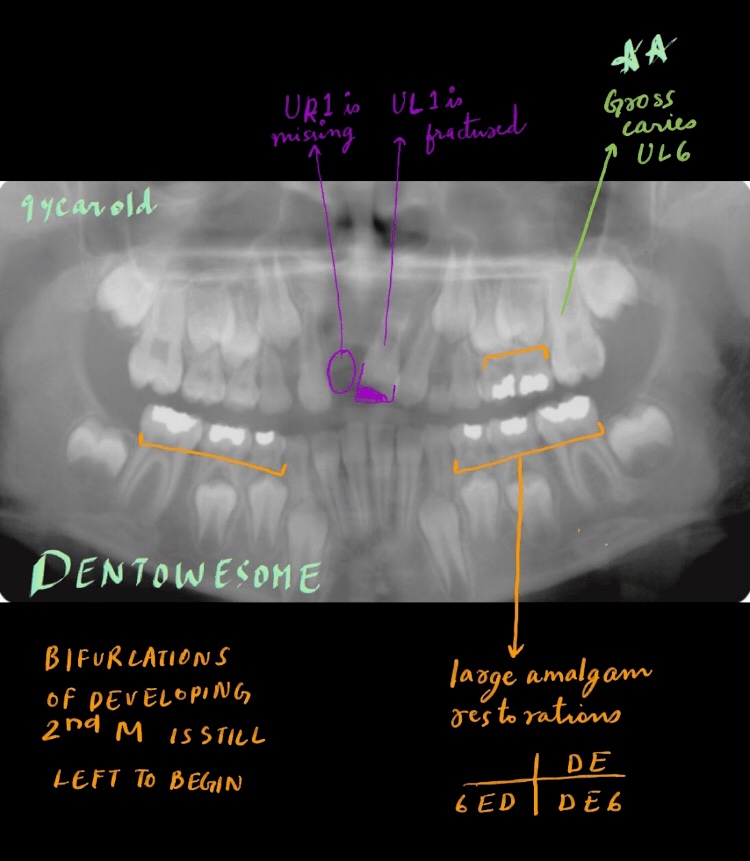
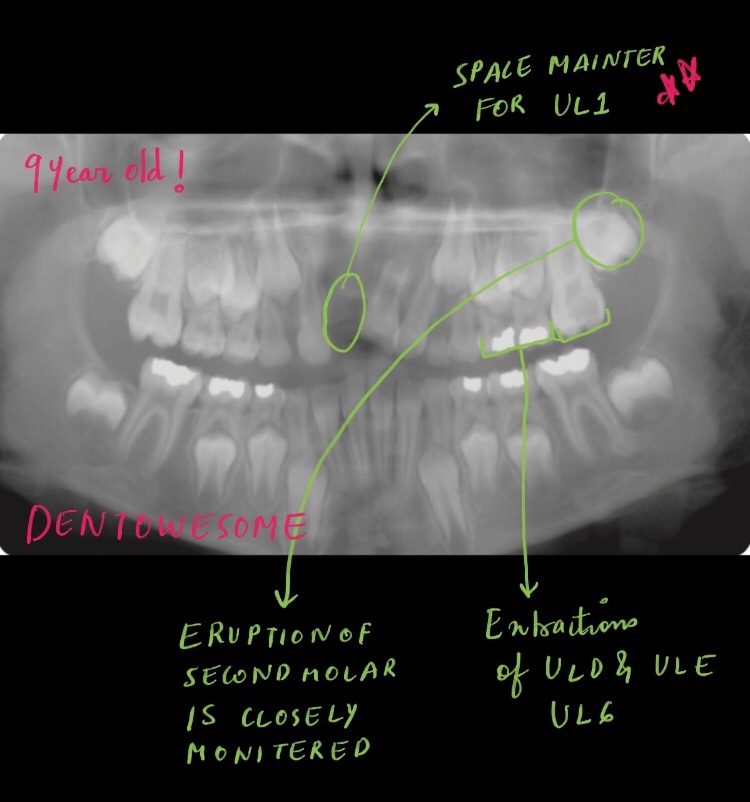
This child presented with significant pain in his upper left dental quadrant. He has an overjet of 8mm, a mild skeletal class II pattern and average vertical proportions, and is still sucking his thumb.
Ortho Case 28
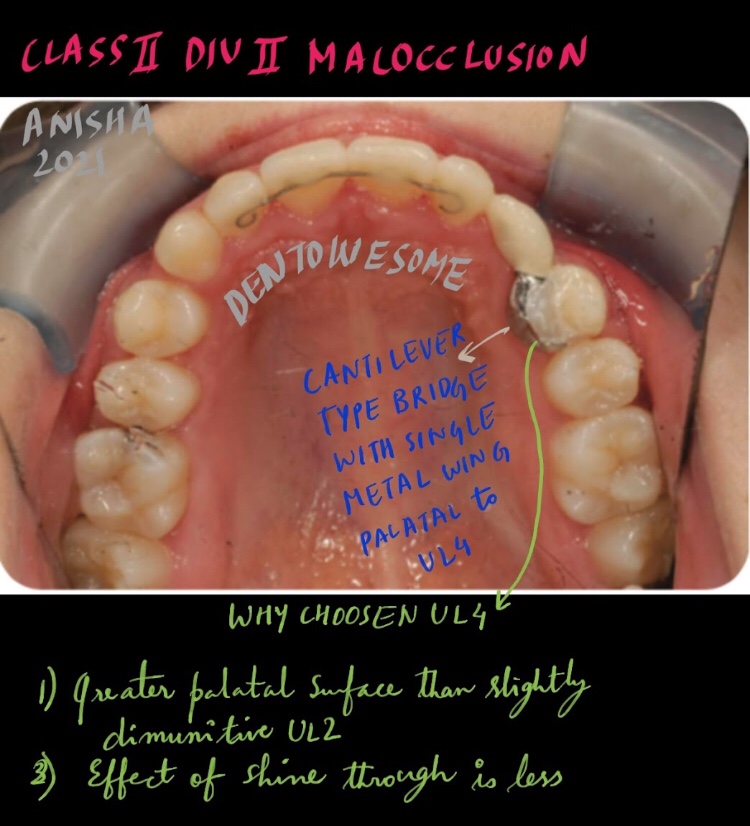
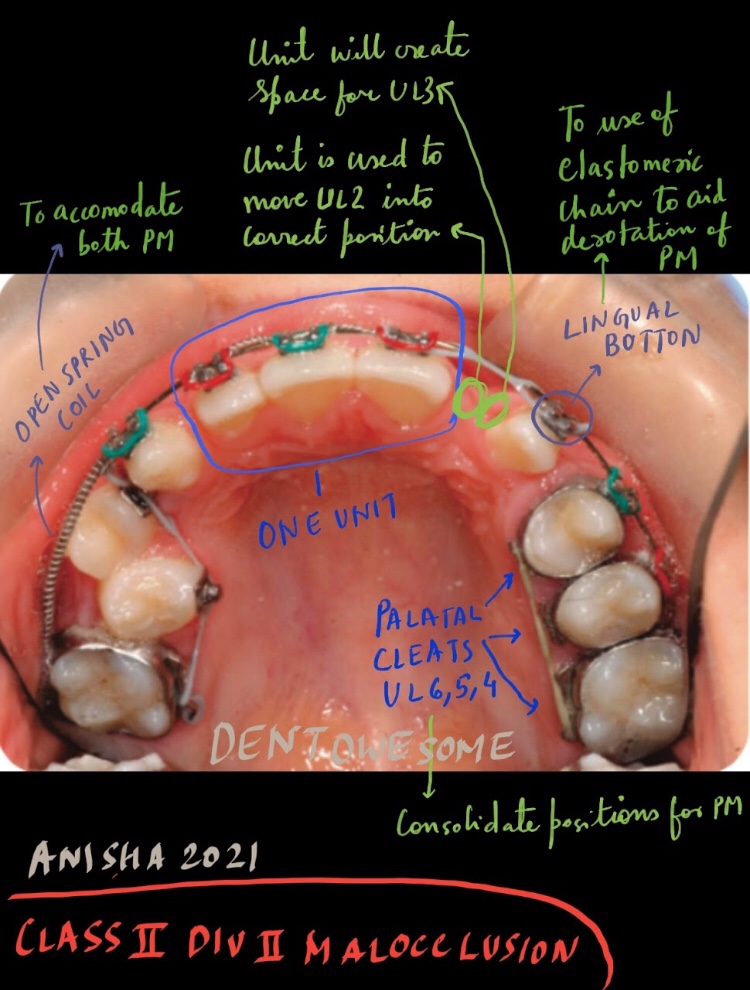
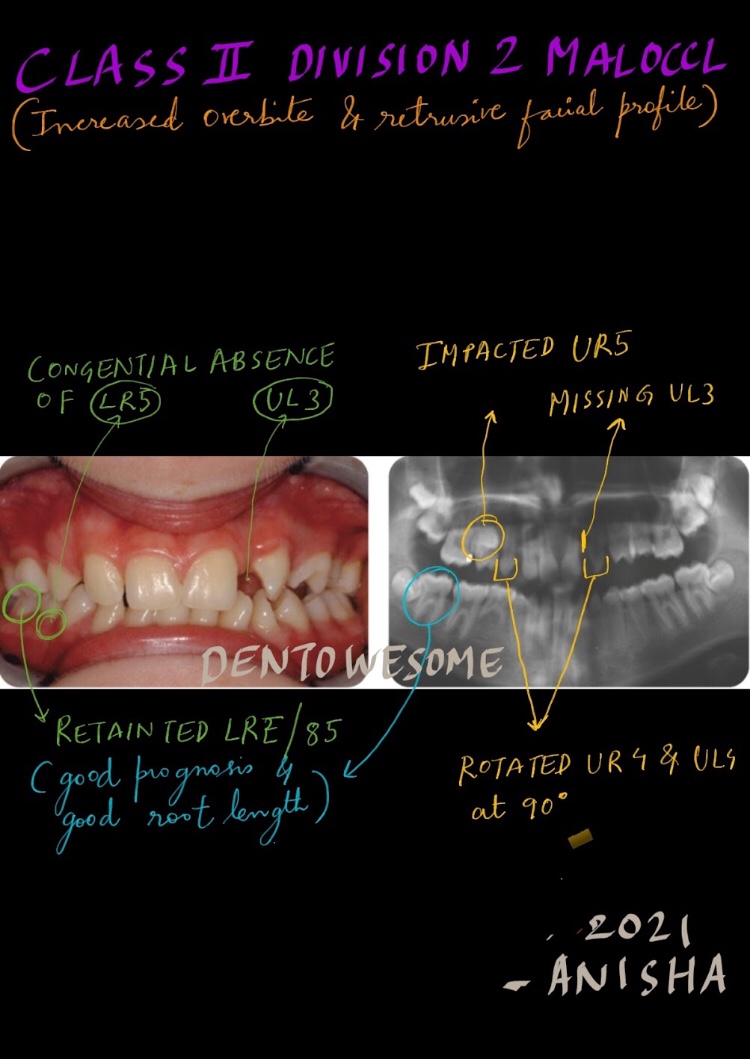
This 12-year-old female presented with a class II division 2 malocclusion on a moderate skeletal class II base with a retrusive profile and agenesis
Link: https://drive.google.com/file/d/1jzdkbvizdmQRovvsN2wBQ8KF42ePM9np/view?usp=drivesdk
Third Year Resources
RESEARCH ARTICLES RELATED TO THE PERIO CASE 7:
1) https://pubmed.ncbi.nlm.nih.gov/8832476/
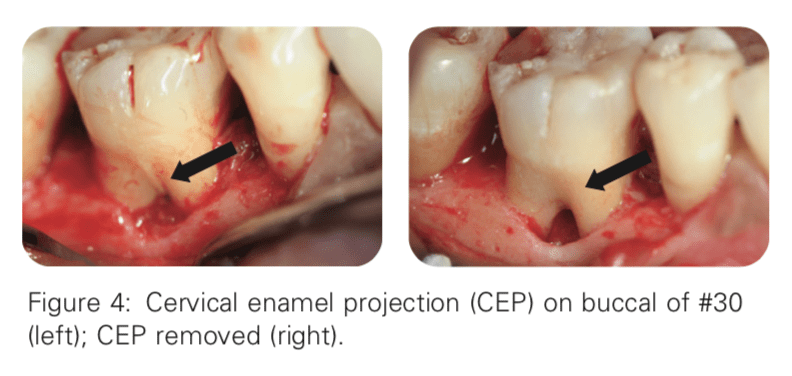
Masters and Hoskins reported that 90% of mandibular furcation invasions have CEPs
2) https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2848791/
Bissada and Abdelmalek reported a 50% correlation between CEPs and furcation invasion
3) https://pubmed.ncbi.nlm.nih.gov/19518034/
The length of root trunk affects attachment loss The longer a given root trunk, the less likely a furcation will be predisposed to attachment loss. Teeth with Taurodontism usually have apically displaced furcation and longer root trunk length
4) https://pubmed.ncbi.nlm.nih.gov/13513891/
Intermediate bifurcation ridges are ridges spanning across the bifurcation of mandibular molars in the mesiodistal direction These ridges are present in 70–77% of the mandibular molars. Just like other anatomic structures, the presence of an intermediate bifurcation ridge may hinder effective plaque control and root preparation by both the patient and dentist
5) https://www.nature.com/articles/bdj.2007.1059
Buccal radicular grooves and palato-gingival grooves are developmental phenomena that affect mainly the maxillary anterior teeth. These grooves run on the roots in the coronal-apical direction Due to their anatomy, the grooves frequently provide a plaque-retentive area that is very difficult to instrument, making teeth with these developmental grooves more prone to attachment loss
Perio Case 7
A 47-year-old female presented with a chief complaint of: “My gums around one of the lower right teeth hurts.” The patient reported soreness and discomfort around tooth #30 from time to time, especially on the buccal side. On occasion, the patient experienced bleeding when brushing her teeth
LEARNING GOALS AND OBJECTIVES
To be able to identify local anatomic factors that may contribute to periodontal disease
To understand the anatomy of the furcation and root
To be able to diagnose a furcation invasion using a furcation classification system


LINK: https://drive.google.com/file/d/1R3qBKH78nqyZ-3Fe4YkvMJjsSbcG9EXw/view?usp=sharing

