Diagnosis Demystified – Case 28

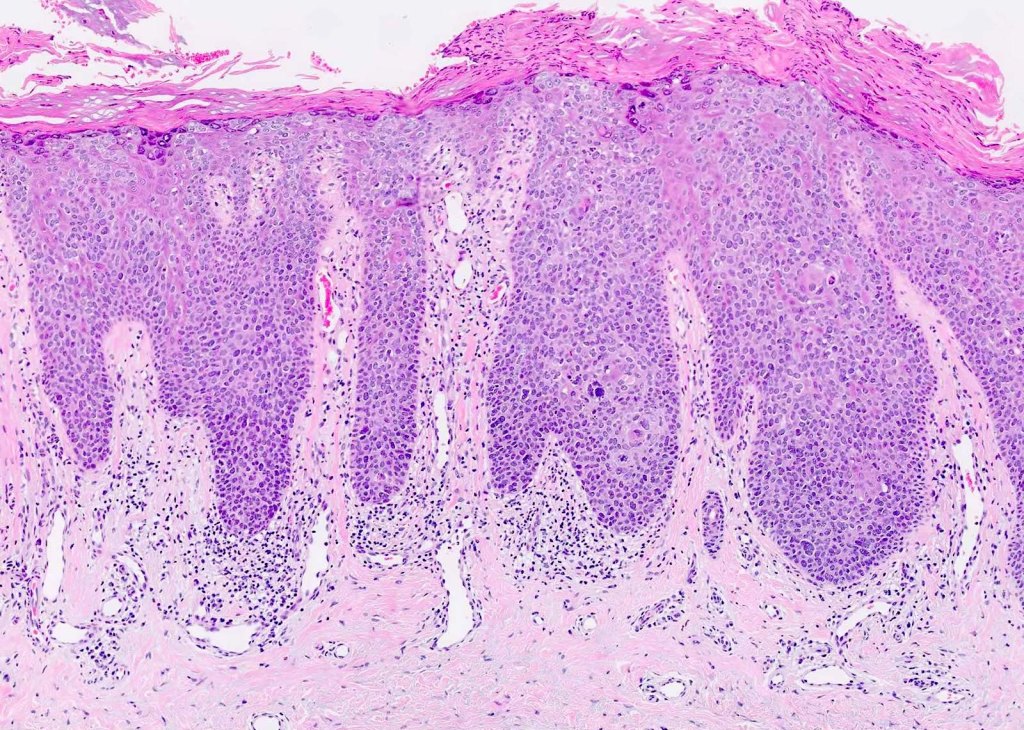
Sections show oral mucosa. In the oral epithelium there is basal-cell crowding and hyperplasia. Atypical mitotic figures are present throughout the thickness of the oral epithelium. The squamous cells show nuclear and cellular pleomorphism, and keratin whorls are present. The rete ridges are drop shaped and individual cell keratinisation is present in some areas.

The diagnosis here is 🔍 Carcinoma in situ! 🦠

In simple terms, it’s like a full-blown drama show happening in the oral epithelium! 🎭 The cells are misbehaving – basal-cell crowding, hyperplasia, and atypical mitotic figures are causing chaos! 🤯🔬

The squamous cells are like divas with nuclear and cellular pleomorphism, and there are even keratin whorls for added glam! 💁‍♀️✨

The rete ridges are shaped like drops, adding some artistic flair, and individual cell keratinisation is stealing the spotlight! 💅🌟

Now, here’s the twist – severe epithelial dysplasia is often considered a prelude to this drama, and together they’re sometimes known as Squamous Intraepithelial Neoplasia Grade 3 (SIN 3)! 📜🌆

Evaluation of the effect of implant angulations and impression techniques on implant cast accuracy

Hey, dental explorers! 🌟 Let’s journey into the captivating realm of implant cast accuracy and the intricate interplay between implant angulations and impression techniques! 🦷🔬

The literature is buzzing with studies unveiling the secrets of digital vs. conventional implant impressions and the impact of those pesky implant angles on accuracy.

📚 Basaki et al. (2017) dived into digital vs. conventional impressions. For digital magic, angulation wasn’t a game-changer. But in the conventional realm, the material, connection type, and a dash of angulation might have stirred the accuracy potion.

Basaki et al. (2017) conducted a study comparing the accuracy of digital and conventional implant impression approaches. They found that for a digital impression approach, where material strain is not a concern, implant angulation did not have a significant influence on impression accuracy. This finding is consistent with previous studies that have also reported no effect of implant angulation on digital impression accuracy. However, the lack of influence on the error in the conventional approach could be potentially explained by the moderate angulation, choice of the impression material, and implant connection type.

🔍 Martínez-Rus et al. (2013) took on multiple implant systems and found metal-splinted direct technique ruling the accuracy charts. The journey went from most accurate to less-so with acrylic resin-splinted, indirect, and unsplinted direct methods.

Martínez-Rus et al. (2013) evaluated the effect of four implant-level impression techniques on the accuracy of definitive casts for a multiple internal connection implant system with different implant angulations and subgingival depths. They found that the metal-splinted direct technique produced the most accurate casts, followed by the acrylic resin-splinted direct, indirect, and unsplinted direct techniques. The study also reported that the accuracy of impressions for internal connection implants decreased as the divergence angle between implants increased.

🔬 Elshenawy et al. (2018) faced angulated implants head-on. Distortion danced with angulation, and unsplinted vs. acrylic resin-splinted techniques fought it out. Up to 15°, direct methods scored in accuracy.

Elshenawy et al. (2018) conducted a study comparing the dimensional accuracy of casts obtained from three impression techniques for three definitive lower casts with implants at different angulations. They found that implant angulation affected the impression accuracy, with increased angulation resulting in increased distortion. The study also reported that the direct unsplinted technique and direct acrylic resin-splinted technique exhibited more accuracy compared to the indirect technique when angulation of implants increased up to 15°.

🌐 Arora et al. (2019) explored parallel vs. angulated implants in the splinted vs. nonsplinted battle. The crown? Splinted technique won in angulated implants, staying true to parallel’s perfection.

Arora et al. (2019) evaluated the accuracy of implant casts generated with splinted and nonsplinted impression techniques with multiple parallel and nonparallel implants. They found that the splinted technique in angulated implants exhibited greater accuracy compared to the nonsplinted technique in parallel implants. This finding was consistent with previous studies that reported less accurate impressions with angulated implants than parallel implants.

📊 Parameshwari et al. (2018) simulated unilateral partially edentulous scenarios. The pick-up technique charmed for multiple angulated implants.

Parameshwari et al. (2018) investigated the effects of implant angulation, type of impression material, and tray selection on impression accuracy in simulated master casts of unilateral partially edentulous situations. They found that there was no statistically significant difference in the accuracy of pick-up non-splinted and transfer techniques when there were three or fewer implants, but the pick-up technique produced superior accuracy for multiple implants with implant angulation more than 20 degrees.

In a nutshell, the harmony of implant cast accuracy is a symphony composed of angulation, impression technique, material, and the magic of digital vs. conventional. Remember, digital might be less angulation-sensitive. And whether you’re picking up or transferring, the choice matters in the land of precision! 🧙‍♀️🏰

Arora, A., Upadhyaya, V., Parashar, K., Malik, D. (2019). Evaluation Of the Effect Of Implant Angulations And Impression Techniques On Implant Cast Accuracy – An In Vitro Study. The Journal of Indian Prosthodontic Society, 2(19), 149. https://doi.org/10.4103/jips.jips_337_18 Basaki, K., Alkumru, H., Souza, G., Finer, Y. (2017). Accuracy Of Digital Vs Conventional Implant Impression Approach: a Three-dimensional Comparative In Vitro Analysis. The International Journal of Oral & Maxillofacial Implants, 4(32), 792-799. https://doi.org/10.11607/jomi.5431 Elshenawy, E., Alam-Eldein, A., Elfatah, F. (2018). Cast Accuracy Obtained From Different Impression Techniques At Different Implant Angulations (In Vitro Study). International Journal of Implant Dentistry, 1(4). https://doi.org/10.1186/s40729-018-0118-6 Martínez-Rus, F., García, C., Santamaría, A., Özcan, M., Pradíes, G. (2013). Accuracy Of Definitive Casts Using 4 Implant-level Impression Techniques In a Scenario Of Multi-implant System With Different Implant Angulations And Subgingival Alignment Levels. Implant Dentistry, 3(22), 268-276. https://doi.org/10.1097/id.0b013e3182920dc5 Parameshwari, G., Chittaranjan, B., Sudhir, N., Ck, A., Taruna, M., M, R. (2018). Evaluation Of Accuracy Of Various Impression Techniques and Impression Materials In Recording Multiple Implants Placed Unilaterally In A Partially Edentulous Mandible- An In Vitro Study. Journal of Clinical and Experimental Dentistry, 0-0. https://doi.org/10.4317/jced.54726

Diagnosis Demystified – Case 27

Histological examination shows sheets of squamous cells supported by fibrous stroma. Keratin pearls are present and there is focal necrosis. The squamous cells are pleomorphic and possess hyperchromatic nuclei. Numerous atypical mitotic figures are present. The invasive front is non-cohesive and there is a moderate chronic inflammatory infiltrate at the invasive front.

Hey, curious minds! 🌟 Let’s dive into some histology secrets! 🕵️‍♀️ Imagine peeping into a microscope and spotting a tissue slide with all the drama – squamous cells forming sheets, keratin pearls, and even focal necrosis! 😱 But that’s not all, the squamous cells look all wild – they’re pleomorphic, with hyperchromatic nuclei and atypical mitotic figures dancing around! 🧪🔬 And guess what? At the front lines, there’s an invasion party going on – non-cohesive and joined by a squad of chronic inflammation! 💥🦠

Hold onto your lab coats, because we’re unveiling the diagnosis – it’s none other than squamous-cell carcinoma! 🦠🔍 This is like a villainous takeover in the world of cells! So, next time you’re in histology class, remember these telltale signs of squamous-cell carcinoma! 📚🩺

RESEARCH – Diagnostic methods and treatment modalities

Squamous-cell carcinoma is a type of oral cancer that can be diagnosed and treated using various options. Diagnostic aids and adjunctive techniques, such as toluidine blue, brush cytology, tissue chemiluminescence, and autofluorescence, can assist in the screening of healthy patients for evidence of cancerous changes or to assess the biologic potential of abnormal mucosal lesions (Lingen et al., 2008). Human papillomavirus (HPV) testing is recommended for oropharyngeal cancer, and treatment options for oropharyngeal squamous-cell carcinoma include radical radiotherapy or transoral surgery and neck dissection (Shah et al., 2016). Additionally, squamous-cell carcinoma of the oral cavity evolves within a field of precancerized oral epithelium, and individuals who have been successfully treated for oral squamous-cell carcinoma are at high risk of developing a recurrence (Feller et al., 2013).

Diagnosis Demystified – Case 26

A longstanding tumour was removed from the parotid gland. The pathologist reported that the tumour was composed of sheets, strands and islands of ductal cells separated by myxochondroid tumour. Plasmacytoid myoepithelial cells were present in some areas and islands of squamous cells were also present. The tumour was enclosed by an intact pseudo- capsule formed by compressed fibrous tissue into which tumour pseudopodia extended.

Hey, peeps! Let’s decode a cool case from the world of dentistry! 🦷🔍 So, there was this long-standing tumor hanging out in the parotid gland. 🤨 The pathologist spilled the tea – the tumor had ductal cells in groups, mixed with myxochondroid stuff! 😲 Plus, there were some plasmacytoid myoepithelial cells hanging around, and even squamous cell islands crashed the party! 🕺🏻💃 The tumor had a slick move too – it had a pseudo-capsule made of tight fibrous tissue!

💪 But guess what? This is known as pleomorphic adenoma, aka a “mixed tumor”! 🎉 ‘Cause it’s a mix of ductal cells and myxochondroid stromal elements! 🧪 And those hyaline plasmacytoid myoepithelial cells? They’re like the signature VIPs of this party! 🤘 Stay tuned for more dental mysteries, y’all! 🌟🦷 #PleomorphicAdenoma #MixedTumorMagic [Link]

RECENT ADVANCES IN PLEOMORPHIC ADENOMA

Pleomorphic adenoma is a common tumor of the salivary glands, particularly the major salivary glands (AlAmari et al., 2021). It typically presents in the third to sixth decades of life (AlAmari et al., 2021). Surgical excision is the mainstay of treatment for pleomorphic adenoma, as these tumors can grow to giant sizes if left untreated (AlAmari et al., 2021). However, recurrent pleomorphic adenoma can be a challenge to treat and has variable outcomes (Kanatas et al., 2018). The recommended treatment for recurrent pleomorphic adenoma includes surgical excision, radiation therapy, or a combination of both (Hemavathy et al., 2022). External beam and neutron radiotherapy may be alternative treatments offered to select patients (Hemavathy et al., 2022).

Recent advances in the diagnosis and treatment of pleomorphic adenoma have focused on improving diagnostic accuracy and refining treatment strategies. Modern imaging techniques, such as MRI, allow for the evaluation of the anatomical extent of the tumor and its relationship to surrounding structures, particularly the facial nerve (Poorten et al., 2011). The World Health Organization (WHO) Histological Classification facilitates accurate and consistent diagnosis of pleomorphic adenoma (Poorten et al., 2011).

In terms of grading and prognostication, there has been a shift in understanding that carcinoma ex pleomorphic adenoma is not automatically a high-grade tumor, as traditionally suggested (Seethala, 2009). Grading schemes for salivary gland carcinomas, including adenoid cystic carcinoma and mucoepidermoid carcinoma, have been developed based on various histological features (Seethala, 2009). These grading schemes help predict the prognosis and guide treatment decisions (Seethala, 2009). Adenoid cystic carcinomas are graded based on the pattern of solid components, with solid components portending a worse prognosis (Seethala, 2009). Mucoepidermoid carcinomas are graded in a three-tier fashion based on various features, including cystic component, border, mitoses, anaplasia, and perineural invasion (Seethala, 2009).

Recent research has also focused on the molecular biology of pleomorphic adenoma. Alterations in the PLAG1 gene have been identified in both benign and malignant pleomorphic adenomas (Martins et al., 2005). These gene alterations play a role in the tumorigenesis of pleomorphic adenoma and may provide insights into the morphogenesis of these tumors (Martins et al., 2005).

In terms of treatment outcomes, postoperative radiotherapy has been shown to improve locoregional control in all stages and grades of parotid carcinoma (Poorten et al., 2011). However, systemic treatment for distant failure remains disappointing, although recent progress in molecular biology has suggested the potential for targeted therapy (Poorten et al., 2011). The prognosis of individual patients can be increasingly accurately predicted through multivariate analysis (Poorten et al., 2011).

In conclusion, recent advances in the diagnosis and treatment of pleomorphic adenoma have focused on improving diagnostic accuracy, refining treatment strategies, and understanding the molecular biology of these tumors. Surgical excision remains the mainstay of treatment, but recurrent pleomorphic adenoma can be challenging to manage. Grading schemes have been developed to predict prognosis and guide treatment decisions for salivary gland carcinomas. Further research is needed to explore targeted therapies and improve outcomes for patients with pleomorphic adenoma.

Cutting-edge tech like MRI and WHO Histological Classification are our allies for precise diagnosis and treatment planning! 📊📸 And guess what? The rulebook for grading and predicting outcomes is getting a makeover! 😲 Carcinoma ex pleomorphic adenoma might not be an automatic baddie – it’s all about those histological features! 📝

We’re delving into the molecular secrets of pleomorphic adenoma with the PLAG1 gene stealing the spotlight! 🧬🔬 Targeted therapy might be the game-changer on the horizon! 🌅 So, while surgery remains the star, the future is filled with potential to conquer these challenges and boost patient outcomes! 🚀

References

AlAmari, K., Zahlan, A., Albawardi, E., Dababo, M., Alotaibi, N. (2021). A Case Report Of a Rare Nasopharyngeal Myoepithelial Dominant Pleomorphic Adenoma. International Journal of Surgery Case Reports, (82), 105859. https://doi.org/10.1016/j.ijscr.2021.105859 Hemavathy, K., V, G., Subramani, V., Susruthan, M. (2022). Recurrent Palatal Pleomorphic Adenoma: a Case Report With A Long-term Follow-up. Cureus. https://doi.org/10.7759/cureus.26363 Kanatas, A., Ho, M., Mücke, T. (2018). Current Thinking About the Management Of Recurrent Pleomorphic Adenoma Of The Parotid: A Structured Review. British Journal of Oral and Maxillofacial Surgery, 4(56), 243-248. https://doi.org/10.1016/j.bjoms.2018.01.021 Martins, C., Fonseca, I., Roque, L., Pereira, T., Ribeiro, C., Bullerdiek, J., … & Soares, J. (2005). Plag1 Gene Alterations In Salivary Gland Pleomorphic Adenoma and Carcinoma Ex-pleomorphic Adenoma: A Combined Study Using Chromosome Banding, In Situ Hybridization And Immunocytochemistry. Modern Pathology, 8(18), 1048-1055. https://doi.org/10.1038/modpathol.3800386 Poorten, V., Bradley, P., Takes, R., Rinaldo, A., Woolgar, J., Ferlito, A. (2011). Diagnosis and Management Of Parotid Carcinoma With A Special Focus On Recent Advances In Molecular Biology. Head & Neck, 3(34), 429-440. https://doi.org/10.1002/hed.21706 Seethala, R. (2009). An Update On Grading Of Salivary Gland Carcinomas. Head and Neck Pathology, 1(3), 69-77. https://doi.org/10.1007/s12105-009-0102-9

Diagnosis Demystified – Case 25

A 55-year-old woman presented to her dentist with carious cavities that had occurred since her last check-up. The patient had noticed that her mouth was dry and, on examination, her parotid glands were enlarged. At the dental hospital, her consultant performed a needle core biopsy, which was reported as containing confluent sheets of non-caseating granulomas. She was referred on to an ophthalamic specialist who found that she had uveitis on slit-lamp examination.

OMG, check out this jaw-dropping dental case, peeps! 🦷💥 This 55-year-old woman rolls into her dentist’s office with cavities, but wait, there’s more drama! 🤯 She’s got a dry mouth and super-sized parotid glands! 🌵💧 Like, what’s going on? 🤷‍♀️ So, she lands in the dental hospital, and her biopsy report comes back with a wild twist – non-caseating granulomas! 😱🔍 But it doesn’t stop there! She’s sent to an ophthalmic specialist and guess what they find? Uveitis on the scene! 👀😓

Whoa, here’s some dental knowledge for you, fam! 🦷💡 Ever heard of Heerfordt’s syndrome? It’s a chronic condition called sarcoidosis, where granulomas go on a wild spree! 🌪️😱 It can hit the parotid glands and cause uveitis, like a double whammy! 👀😓 But wait, there’s more! Facial nerve palsy and fever might join the party too! 🤧🌡️ So, next time you spot this dental detective, think Heerfordt’s syndrome! 🔍💙

Heerfordt’s syndrome, also known as Heerfordt-Waldenström syndrome or uveoparotid fever, is a rare subtype of sarcoidosis. It is characterized by the presence of parotid gland enlargement, facial nerve palsy, uveitis, and low-grade fever (Sève et al., 2021; Denny & Fotino, 2013; Kakizaki et al., 2017; Fujiwara et al., 2016). Complete Heerfordt’s syndrome is diagnosed when all four main symptoms are present, while incomplete Heerfordt’s syndrome is diagnosed when two out of the three symptoms (facial nerve palsy, parotid gland enlargement, and anterior uveitis) are detected (Ahmed et al., 2020; Fujiwara et al., 2016).

The most common symptoms of Heerfordt’s syndrome are facial nerve palsy, parotid gland enlargement, and anterior uveitis (Sève et al., 2021; Denny & Fotino, 2013; Kakizaki et al., 2017; Fujiwara et al., 2016). Other possible manifestations of sarcoidosis include cough, dyspnea, chest pain, weight loss, arthralgias, erythema nodosum, and intrathoracic involvement (Denny & Fotino, 2013; Sève et al., 2021). Intrathoracic involvement, characterized by symmetrical bilateral hilar adenopathy and/or diffuse lung micronodules, is the most common extrapulmonary manifestation of sarcoidosis (Denny & Fotino, 2013). Skin lesions, liver or splenic involvement, peripheral and abdominal lymphadenopathy, and peripheral arthritis are also frequent extrapulmonary manifestations (Denny & Fotino, 2013).

Heerfordt’s syndrome is typically self-limiting and resolves within 12 to 36 months, although some cases may be prolonged (Kakizaki et al., 2017).

Heerfordt’s syndrome – It’s a sneaky subtype of sarcoidosis. 👀🤒 The main players are parotid gland enlargement, facial nerve palsy, uveitis, and a low-grade fever! 🔍🌡️ When all four symptoms party together, it’s complete Heerfordt’s syndrome, but even with two out of three, it’s still incomplete! 🤝🏽💫 Other possible signs include cough, chest pain, weight loss, and more! So keep your eyes peeled for this rare gem! 💎✨ It usually clears up within a year or so, but some cases can be trickier! 🕰️💙

An In-Vivo Study compared the effectiveness of single-sitting endodontic therapy in primary mandibular molar using rotary and hand instruments

Hey, dental enthusiasts! 🌟 Let’s talk endodontic therapy and the power of different instrumentation techniques! 🦷💪

One study compared Mtwo and ProTaper rotary systems with manual instruments in primary teeth. Guess what? No big differences in cleaning efficiency! 😮 But ProTaper was better in the coronal and middle thirds than the apical third! 🔄🎯 Another study checked out continuous rotary, reciprocating rotary, and manual instruments in primary molars. Rotary instruments took the lead! They provided superior canal cleanliness, faster prep time, and better shaping efficacy! 🏆🌀 And rotary instruments have even more perks! They’re more convenient, making them perfect for kids’ root canal treatment! 🧒👌 Plus, they cause fewer canal issues and maintain better centering than hand instruments! 🎉🚀 But don’t worry, fam! Manual and rotary techniques are both safe for primary molars with no significant root resorption! 🌈 So, whether it’s manual or rotary, you’ve got options to rock those root canals! 🎸💙 Stay tuned for more dental updates! 😁✨

In the field of endodontic therapy, the effectiveness of different instrumentation techniques has been a topic of interest. One study by compared the cleaning capacity of two rotary systems, Mtwo and ProTaper, with manual instruments in primary teeth (Azar et al., 2012). The study found that there were no significant differences in cleaning efficiency between manual and rotary instruments. However, ProTaper files performed better in the coronal and middle thirds of the root canal compared to the apical third (Azar et al., 2012). Another study by investigated the cleaning efficacy, shaping ability, preparation time, and file deformation of continuous rotary, reciprocating rotary, and manual instrumentations in primary molars (Ramazani et al., 2016). The study found that rotary instrumentation provided superior canal cleanliness and required less time for completion of canal preparation compared to manual instrumentation (Ramazani et al., 2016). Additionally, the study found that reciprocating rotary instruments displayed better shaping efficacy compared to manual instruments (Ramazani et al., 2016).

Furthermore, the use of rotary instruments in endodontic treatment has several advantages. found that rotary files are more convenient to use and can facilitate root canal preparation, making them more appropriate for use in children (Mehlawat et al., 2019). Additionally, rotary instruments have been shown to cause fewer canal transportation and maintain better canal centering compared to hand instruments (Goel et al., 2019). This is important for successful root canal treatment as efficient canal preparation is key (Ramazani et al., 2016).

In terms of primary molars, the effectiveness of different instrumentation techniques has also been studied. A study by compared the effectiveness of manual and rotary instrumentation techniques in primary molars (Daher et al., 2015). The study found that both manual and rotary instrumentation techniques were safe procedures for primary molars without significant root resorption (Daher et al., 2015). Another study by compared the cleaning efficacy, shaping ability, preparation time, and file deformation of different instrumentation techniques in primary molars (Ramazani et al., 2016). The study found that rotary files exhibited greater potential in terms of cleaning efficacy, shaping ability, and preparation time compared to manual files (Ramazani et al., 2016). Additionally, the study found that reciprocating rotary instruments displayed better shaping efficacy compared to manual instruments (Ramazani et al., 2016).

Overall, the studies suggest that rotary instrumentation techniques, such as the use of Mtwo, ProTaper, and reciprocating rotary files, can provide effective cleaning and shaping of root canals in primary molars. These techniques offer advantages such as better canal cleanliness, shorter treatment times, and improved shaping efficacy compared to manual instrumentation. However, it is important to consider individual patient factors and the specific characteristics of the tooth being treated when selecting the appropriate instrumentation technique.

Azar, M., Safi, L., Nikaein, A. (2012). Comparison Of the Cleaning Capacity Of Mtwo And Protaper Rotary Systems And Manual Instruments In Primary Teeth. Dental Research Journal, 2(9), 146. https://doi.org/10.4103/1735-3327.95227 Daher, A., Viana, K., Leles, C., Costa, L. (2015). Ineffectiveness Of Antibiotic-based Pulpotomy For Primary Molars: a Survival Analysis. Pesquisa Brasileira Em Odontopediatria E Clínica Integrada, 1(15), 205-215. https://doi.org/10.4034/pboci.2015.151.22 Goel, A., Tikku, A., Chandra, A. (2019). Comparative Evaluation Of Canal Transportation and Centering Ability Of Three Single File Systems. Ip Indian Journal of Conservative and Endodontics, 3(4), 86-90. https://doi.org/10.18231/j.ijce.2019.020 Mehlawat, R., Kapoor, R., Gandhi, K., Kumar, D., Malhotra, R., Ahuja, S. (2019). Comparative Evaluation Of Instrumentation Timing and Cleaning Efficacy In Extracted Primary Molars Using Manual And Niti Rotary Technique – Invitro Study. Journal of Oral Biology and Craniofacial Research, 2(9), 151-155. https://doi.org/10.1016/j.jobcr.2019.03.003 Ramazani, N., Mohammadi, A., Amirabadi, F., Ramazani, M., Ehsani, F. (2016). In Vitro Investigation Of the Cleaning Efficacy, Shaping Ability, Preparation Time And File Deformation Of Continuous Rotary, Reciprocating Rotary And Manual Instrumentations In Primary Molars. Journal of Dental Research Dental Clinics Dental Prospects, 1(10), 49-56. https://doi.org/10.15171/joddd.2016.008

Influence of heat treatment of nickel–titanium instruments on the accuracy of an electronic apex locator integrated with endodontic motor.

The influence of heat treatment of nickel-titanium (NiTi) instruments on the accuracy of electronic apex locators (EALs) integrated with endodontic motors has been the subject of several studies. Gavini et al. (2022)conducted a study to evaluate the influence of different heat treatments of NiTi instruments and the diameter of the apical preparation on the accuracy of an EAL used during root canal preparation. The study found that the heat treatment and the diameter of the apical preparation did not influence the accuracy of working length determination by an EAL integrated with the endodontic motor (Gavini et al., 2022).

Heo et al. (2022) investigated the accuracy of two electronic apex locators (DentaPort and Bingo) using heat-treated NiTi files. The study compared the true root canal length determined using K files with the electronically measured length using two different NiTi files (ProGlider and HyFlex EDM Glide Path File) and two electronic apex locators. The results showed that there was no significant difference between the measurements with different NiTi files or electronic apex locators, and all differences between the true root canal length and electronically measured length were within ±0.5 mm (Heo et al., 2022).

Similarly, Sadeghi & Abolghasemi (2010) evaluated the accuracy of the Raypex5 electronic apex locator using stainless-steel hand K-files versus nickel-titanium rotary Mtwo files. The study aimed to assess the accuracy of the apex locator when different types of files were used interchangeably. The results showed that there was no significant difference in accuracy between the two types of files (Sadeghi & Abolghasemi, 2010).

Overall, the available literature suggests that the heat treatment of NiTi instruments does not significantly affect the accuracy of electronic apex locators in determining the working length during root canal preparation. The accuracy of electronic apex locators is not adversely affected by the presence of irrigation solutions used during root canal therapy (Al-Hadlaq, 2011). These findings provide reassurance to clinicians regarding the accuracy and reliability of electronic apex locators integrated with endodontic motors in determining the working length during root canal treatment.

Diagnosis Demystified – Case 24

A 56-year-old woman complains of a burning sensation affecting her tongue. It is present on a more or less continuous basis and gets worse as the day goes on. Her GP prescribed a mouthwash for her but this has not been of any benefit. She is edentulous but leaving her dentures out makes no difference to the pain. Her medical history is unremarkable and, on examination, her tongue appears completely normal. What is the diagnosis? Click on below link to find out the answer

Hey, guys! 🙋‍♀️ So, there’s this 56-year-old lady, and she’s like, “My tongue feels like it’s on fire 🔥 all the time, ugh!” Her GP gave her this lame mouthwash, but it’s like, zero help. 🙅‍♀️ Like, why even bother, right? She doesn’t even have teeth, and guess what? Taking out her dentures doesn’t make a dang difference to the pain! 😬 Her medical history is all chill, and when they checked her tongue, it’s totally normal. 🤷‍♀️ So, what could be causing this burning sensation? It’s like a mystery, y’all! 🕵️‍♀️

So, like, if you’re on the same page as me, you’re probably DYING to know the diagnosis, right?! I gotchu covered! Just click on the link below to reveal the big answer! 🕵️‍♀️

Alright, brace yourselves for the big reveal! 🥁 drumroll, please 🥁 The diagnosis is… (wait for it) … Burning Mouth Syndrome (BMS)! 🙌 Yeah, you heard me right! It’s this condition where you feel this burning sensation in your mouth, but there’s no apparent cause! 😵

I know, I know, it’s like, totally insane! 😜 But BMS is for real, yo! It’s this mysterious thing that can happen to anyone, even if they don’t have teeth! 🦷 It’s like your taste buds are throwing a party, but instead of fun, it’s just burning vibes. 🔥 And it’s not just her, peeps! Lots of people deal with this, and it can be super frustrating! 😤

So, even though her mouth looks fine, she’s stuck with this annoying burning sensation. 🙅‍♀️ But don’t worry, she’s not alone! There are ways to manage this crazy BMS beast, like staying away from spicy foods or acidic stuff that can make it worse. 😓

RESEARCH

Burning Mouth Syndrome (BMS) is a chronic oral pain disorder characterized by a burning sensation in the mouth without any specific mucosal lesions (Kim et al., 2020). It is more common in women, particularly in the fourth to sixth decades of life (Scardina et al., 2010). The exact cause of BMS is still unknown, but it has been associated with various factors such as psychoneurological conditions, peripheral nerve atrophy in the tongue epithelium, and psychosocial events (Kim et al., 2020).

Several studies have reported an increased prevalence of psychiatric symptoms and psychological disorders in patients with BMS, including depression and anxiety (Kim et al., 2020). In a population-based cohort study conducted in South Korea, it was found that patients with BMS had a higher risk of developing depression and anxiety compared to individuals without BMS (Kim et al., 2020). The adjusted hazard ratios for the development of depression and anxiety were 2.77 and 2.42, respectively (Kim et al., 2020).

In addition to psychiatric symptoms, BMS has also been associated with other chronic pain syndromes, such as other idiopathic orofacial pain and central sensitivity syndromes (Moisset et al., 2016). This suggests that BMS may share common mechanisms with other chronic pain conditions (Moisset et al., 2016).

Treatment options for BMS are limited and there is no gold-standard treatment available (Çinar et al., 2018). However, various approaches have been explored. One study evaluated the efficacy of a topical capsaicin rinse in improving the symptoms of BMS and found it to be useful in treating the discomfort associated with BMS (Silvestre et al., 2012). Another study investigated the effectiveness and safety of clonazepam, pregabalin, and alpha-lipoic acid for treating BMS and found that systemic clonazepam and pregabalin were viable options for treatment (Çinar et al., 2018). Acupuncture has also been suggested as a therapeutic possibility for BMS (Scardina et al., 2010).

In conclusion, BMS is a chronic oral pain disorder characterized by a burning sensation in the mouth. It is associated with an increased risk of developing psychoneurological conditions, such as depression and anxiety. The exact cause of BMS is still unknown, but it has been linked to peripheral nerve atrophy, psychosocial events, and other chronic pain syndromes. Treatment options for BMS are limited, but topical capsaicin, systemic clonazepam, pregabalin, and alpha-lipoic acid have shown promise in improving symptoms. Further research is needed to better understand the etiology and develop more effective treatments for BMS.

REFERENCES

Kim, Y., Ko, I., Kim, D. (2020). Association Between Burning Mouth Syndrome and The Development Of Depression, Anxiety, Dementia, And Parkinson Disease. JAMA Otolaryngol Head Neck Surg, 6(146), 561. https://doi.org/10.1001/jamaoto.2020.0526 Moisset, X., Calbacho, V., Torres-Martínez, P., Gremeau-Richard, C., Dallel, R. (2016). Co-occurrence Of Pain Symptoms and Somatosensory Sensitivity In Burning Mouth Syndrome: A Systematic Review. PLoS ONE, 9(11), e0163449. https://doi.org/10.1371/journal.pone.0163449 Scardina, G., Ruggieri, A., Provenzano, F., Messina, P. (2010). Burning Mouth Syndrome: Is Acupuncture a Therapeutic Possibility?. Br Dent J, 1(209), E2-E2. https://doi.org/10.1038/sj.bdj.2010.582 Silvestre, F., Silvestre-Rangil, J., Tamarit-Santafé, C., Bautista, D. (2012). Application Of a Capsaicin Rinse In The Treatment Of Burning Mouth Syndrome. Med Oral, e1-e4. https://doi.org/10.4317/medoral.17219 Çinar, S., Kartal, D., Pergel, T., Borlu, M. (2018). Effectiveness and Safety Of Clonazepam, Pregabalin, And Alpha Lipoic Acid For The Treatment Of Burning Mouth Syndrome. Erciyes Med J, 35-38. https://doi.org/10.5152/etd.2018.17160
Comparative evaluation of postoperative pain following chemomechanical preparation of single-rooted nonvital teeth with symptomatic apical periodontitis with and without laser irradiation

Hey, peeps! 🌟 Let’s talk about postoperative pain in those endodontic procedures! 😫 Ouch, right? But guess what? There are some cool ways to reduce that pain! 🙌💙 One factor is how they clean and shape those root canals – it can release irritants and cause inflammation! 🔍😓 But fear not, studies have looked into different techniques to make it less painful! 😎 Like keeping the apical patency during the cleaning process – it didn’t make a big difference in pain! 🚫🦷 And using laser irradiation as an add-on – whoa, it actually helped reduce post-op pain! 🔥💡 Even the form of sodium hypochlorite (NaOCI) they use matters! But whether it’s gel or solution, post-op pain is kinda similar! 🤷‍♀️💦 Also, the size of apical preparation – it didn’t affect pain much either! 😅🔄 So, it’s like a puzzle, fam! There’s no one-size-fits-all solution, and they need to pick the best pain relief for each case! 🧩💊

Postoperative pain is a common concern in endodontic procedures, and various factors can contribute to its occurrence. One important factor is the chemomechanical preparation of the root canals, which can lead to the release of irritants and induce an acute inflammatory response in periapical tissues (Machado et al., 2022; Uysal et al., 2022; Adigüzel et al., 2019). The presence of residual infection after chemomechanical preparation can also contribute to postoperative pain (Shivangi et al., 2022). Therefore, it is crucial to evaluate different techniques and adjuncts that can potentially reduce postoperative pain in endodontic procedures.

One study compared the effect of maintaining apical patency during chemomechanical preparation on postoperative pain in posterior teeth with necrotic pulps and apical periodontitis. The study found that maintaining apical patency had no significant influence on postoperative pain in these cases (Arora & Duhan, 2015). Another study compared the postoperative pain intensity after using reciprocating and continuous rotary glide path systems for glide path preparation. The study found that there was no significant difference in postoperative pain intensity between the two systems (Adigüzel et al., 2019).

Laser irradiation has also been investigated as an adjunct to reduce postoperative pain in endodontic procedures. A double-blind randomized placebo-controlled clinical trial compared postoperative pain following chemomechanical preparation with and without laser irradiation in nonvital teeth with symptomatic apical periodontitis. The study found that laser irradiation led to a significant reduction in postoperative pain (Machado et al., 2022; Shivangi et al., 2022).

The form of sodium hypochlorite (NaOCI) used during chemomechanical preparation has also been studied in relation to postoperative pain. A randomized clinical trial compared the effect of using gel and solution forms of NaOCI on postoperative pain. The study found that the use of the gel form of NaOCI showed similar postoperative pain compared to the solution form (Özlek et al., 2021).

Furthermore, the size of apical preparation has been investigated in relation to postoperative pain. One study evaluated postoperative pain after endodontic treatment of necrotic teeth submitted to large apical preparation using oscillatory kinematics. The study found no significant difference in postoperative pain between teeth with and without large apical preparation (Machado et al., 2022; Machado et al., 2021).

In addition to the techniques and adjuncts used during chemomechanical preparation, the choice of analgesics can also affect postoperative pain. A study compared local and systemic ibuprofen for the relief of postoperative pain in symptomatic teeth with apical periodontitis. The study aimed to determine the most effective method for relieving postoperative pain due to chemomechanical preparation (Uysal et al., 2022).

Overall, the management of postoperative pain in endodontic procedures is a multifactorial process. Factors such as the technique and adjuncts used during chemomechanical preparation, the form of irrigants, the size of apical preparation, and the choice of analgesics can all influence postoperative pain. It is important for clinicians to consider these factors and tailor their approach to each individual case to minimize postoperative pain and improve patient comfort.

REFERENCES

Adigüzel, M., Yılmaz, K., Tufenkci, P. (2019). Comparison Of Postoperative Pain Intensity After Using Reciprocating and Continuous Rotary Glide Path Systems: A Randomized Clinical Trial. Restor Dent Endod, 1(44). https://doi.org/10.5395/rde.2019.44.e9 Arora, M., Duhan, J. (2015). Effect Of Maintaining Apical Patency On Endodontic Pain In Posterior Teeth With Pulp Necrosis and Apical Periodontitis: A Randomized Controlled Trial. Int Endod J, 4(49), 317-324. https://doi.org/10.1111/iej.12457 García-Font, M., Duran-Sindreu, F., Calvo, C., Basilio, J., Abella, F., Ali, A., … & Olivieri, J. (2017). Comparison Of Postoperative Pain After Root Canal Treatment Using Reciprocating Instruments Based On Operator’s Experience: a Prospective Clinical Study. J Clin Exp Dent, 0-0. https://doi.org/10.4317/jced.54037 Machado, R., Comparin, D., Ignácio, S., Mx, N. (2022). Postoperative Pain After Endodontic Treatment Of Necrotic Teeth Submitted To Large Apical Preparation Using Oscillatory Kinematics. J Clin Exp Dent, e158-e167. https://doi.org/10.4317/jced.58726 Machado, R., Comparin, D., Ignácio, S., Neto, U. (2021). Postoperative Pain After Endodontic Treatment Of Necrotic Teeth With Large Intentional Foraminal Enlargement. Restor Dent Endod, 3(46). https://doi.org/10.5395/rde.2021.46.e31 Opacic-Galic, V., Zivkovic, S. (2011). Postoperative Pain After Primary Endodontic Treatment and Retreatment Of Asimptomatic Teeth. SERBIAN DENT J, 2(58), 75-81. https://doi.org/10.2298/sgs1102075p Shivangi, S., Rao, R., Jain, A., Verma, M., Guha, A., Langade, D. (2022). Comparative Evaluation Of Postoperative Pain Following Chemomechanical Preparation Of Single-rooted Nonvital Teeth With Symptomatic Apical Periodontitis With and Without Laser Irradiation: A Double-blind Randomized Placebo Controlled Clinical Trial. J Conserv Dent, 6(25), 610. https://doi.org/10.4103/jcd.jcd_276_22 Uysal, İ., Eratilla, V., Topbaş, C., Çelik, Y. (2022). Comparison Of Local and Systemic Ibuprofen For Relief Of Postoperative Pain In Symptomatic Teeth With Apical Periodontitis. Med Sci Monit, (28). https://doi.org/10.12659/msm.937339 Özlek, E., Gunduz, H., Kadi, G., Tasan, A., Akkol, E. (2021). The Effect Of Solution and Gel Forms Of Sodium Hypochlorite On Postoperative Pain: A Randomized Clinical Trial. J. Appl. Oral Sci., (29). https://doi.org/10.1590/1678-7757-2020-0998